Two vaccine candidates designed specifically for Bundibugyo virus disease are expected to join an ongoing clinical trial during the current Ebola outbreak in the Democratic Republic of the Congo. The step is important because there is no licensed vaccine specifically approved for disease caused by Bundibugyo virus.
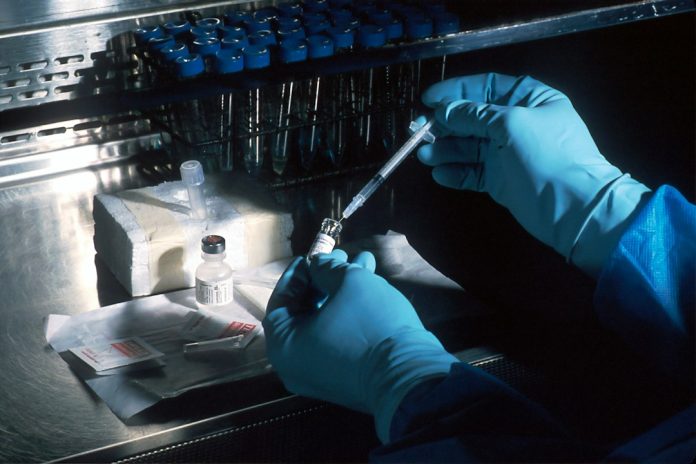
The candidates are ChAdOx1-BDBV, developed by the University of Oxford with the Serum Institute of India, and mRNA-1469, developed by Moderna. An independent technical advisory group convened by the World Health Organization recommended both for further clinical evaluation after reviewing available preclinical and early clinical evidence.
The recommendation does not mean that either vaccine has been proven effective. Both remain investigational and will enter the trial only after national approvals and the required ethical and regulatory steps.
Why the virus species matters
Ebola disease can be caused by several related viruses. A vaccine that works against one species cannot automatically be assumed to protect against another. Ervebo, the licensed and WHO-prequalified vaccine used against Zaire ebolavirus, is not specifically licensed for Bundibugyo virus disease.
The current research program is therefore evaluating whether existing approaches offer useful protection and whether new candidates designed for Bundibugyo virus can generate stronger evidence.
How the Tumaini trial works
The Tumaini clinical trial is designed to evaluate multiple vaccine candidates within one research platform. It uses a ring-vaccination strategy, enrolling contacts of people with confirmed Bundibugyo virus disease and, depending on the protocol, contacts of those contacts.
Ring vaccination concentrates the study around people at higher risk of exposure during an outbreak. The approach was used in research during the West Africa Ebola epidemic and contributed to evidence supporting Ervebo against Zaire ebolavirus.
Four vaccination rings were already operating when the WHO announced the new recommendations, with additional rings being prepared. The trial is led by the Democratic Republic of the Congo’s Institut National de Recherche Biomédicale with support from international research and public-health partners.
What is known about the candidates
ChAdOx1-BDBV uses a viral-vector platform related to technologies previously studied for other infectious diseases. mRNA-1469 uses an mRNA platform. The WHO advisory group reviewed available information on manufacturing, preclinical studies and early human safety and immune-response data.
Early evidence can show whether a candidate produces an immune response and whether immediate safety signals are acceptable in a limited group. It cannot establish how well the vaccine prevents disease during real-world exposure. That requires a larger clinical trial with carefully defined outcomes.
What the trial still needs to answer
The central question is vaccine efficacy: whether vaccination reduces the risk of developing Bundibugyo virus disease after exposure. Researchers will also continue to assess safety, the strength and durability of immune responses, and the practical requirements for delivering each vaccine during an outbreak.
Results may depend on the number of eligible participants, the pattern of transmission and how quickly vaccination occurs after a case is identified. Outbreak trials are scientifically valuable but operationally difficult because public-health teams must protect communities while maintaining rigorous research procedures.
Treatment research is moving in parallel
Vaccine research is only one part of the response. A separate WHO-sponsored trial is evaluating potential treatments for confirmed Bundibugyo virus disease. Investigational options include the monoclonal antibody MBP134, the antiviral remdesivir and combinations of those approaches. Other products are also being added or studied for treatment and post-exposure prevention.
These studies are not evidence that a particular treatment already works. They are structured efforts to determine whether the candidates improve survival or prevent illness.
Vaccines cannot replace outbreak control
Even a successful vaccine would not replace the core measures used to control Ebola outbreaks. Rapid case identification, safe clinical care, laboratory confirmation, contact tracing, infection prevention, community engagement and safe burial practices remain essential.
Vaccination can become an additional layer when evidence supports its use. Until then, trial participation must follow informed-consent, safety-monitoring and ethical-review requirements.
How to interpret the announcement
The inclusion of two additional candidates shows that vaccine development has progressed far enough for evaluation during an active outbreak. It does not mean the vaccines are available for routine use, and it does not establish that one platform is superior.
WHO expects initial treatment findings in the coming months and vaccine-trial results in early 2027. Timelines may change as the outbreak and enrollment evolve.
For the public, the most accurate message is cautious: two promising vaccine candidates are moving into a trial designed to generate the evidence that is still missing. Any decision about wider use will depend on the trial’s safety and efficacy results and on national and international regulatory review.